Edition 1.5: Governance Divergence and System Behaviour across Saudi Arabia & MENA - Structural Realities of Saudi-MENA Sport Systems
Edition 1.5: Governance divergence and system behaviour across Saudi Arabia & MENA Structural Realities of Saudi-MENA Sport Systems
Edition 1.5
After reading the precursor to this post - UK Sports Institute (UKSI) Performance Systems: Saudi–MENA Governance Adaptation - this follows with another deeper version that was published on Substack on May 05, 2026.
Edition 1.5: Governance divergence and system behaviour across Saudi Arabia and MENA - Structural Realities of Saudi–MENA Sport Systems. First published on Substack on May 05, 2026.
Formatting note
A formatting issue in the initial distribution affected the presentation of structural elements. This has now been corrected in the live edition, restoring the intended frameworks and comparisons.
Saudi sport is entering a new phase defined by governance reform, capability development and system‑level design. This edition examines the divergence between UK Sport Institute (UKSI) governance models and the structural and operational realities across Saudi Arabia and the wider MENA region, and the implications for federations navigating evolving national priorities.
1. Governance Reality: How Saudi and Jordan (MENA) Sport Actually Works
UKSI models were built inside a mature, decentralised, athlete‑centred ecosystem with stable governance, integrated data, and clear clinical decision rights. Saudi and wider MENA sport operate at a different governance altitude. Authority flows vertically through ministries, the Saudi Olympic and Paralympic Committee, federations, and clubs. Approvals move through hierarchy and relationships, and medical decisions often require executive or CEO‑level confirmation.
Where UKSI models are built around autonomy, horizontal integration and athlete‑centred clinical governance, Saudi systems are shaped by leadership, institutional priorities and developing structures. Pathways differ between clubs, federations, and ministries. Data democratisation is hierarchical and often held at executive level. Data in emerging envionments is frequently fragmented or manual, systems sit across multiple platforms, team and athlete data literacy is uneven, and the pipelines that UK and European models rely on do not yet exist or are emerging at different speeds.
Athlete injury assessment, protocols, communication and decisions reflect organisational considerations as much as clinical ones. Medical governance in Saudi and MENA operates inside relationship‑based and hierarchical structures rather than independent clinical pathways. Effective performance and medical systems must therefore be designed for the governance environment that exists today in Saudi and MENA sport, not for UK or European contexts.
2. The Hierarchical Governance Framework

Figure 1. Structural contrast between athlete-centred UKSI pathways and vertically governed Saudi–MENA systems, highlighting differences in authority, data flow and decision-making.
2.1 Governance Mechanisms in Emerging Systems

Table 1. Governance diversity across GCC and MENA and its impact on policy, access, and performance system delivery
Governance across Saudi Arabia and the wider MENA region is still emerging, with reporting lines and protocols forming as clubs and organisations professionalise. Director‑level performance and medical roles are developing, and authority remains concentrated at senior levels.
Integrated working became possible through consistent delivery, technical competence and collaboration with Team Managers, who act as connectors between executive leadership, internal and external medical providers, and national teams. This approach respected approval lines while modelling the behaviours required for more stable governance.
2.3 Bilateral Flow and Decision Support
Team Managers provided a second set of back channels to executive leadership. Information moved vertically to senior decision‑makers, but also returned down to Director level, supporting:
- nuance
- cultural intelligence
- context
- diplomacy
- strategic alignment
- precise decision‑making
This bilateral flow strengthened delivery and reinforced trust in the performance and medical functions. In hierarchical systems, these relationships ensure that technical and medical information reaches leadership with the nuance required for informed and timely decisions.
2.4 The Role of Cultural Intelligence (CQ)
Cultural Intelligence enables practitioners to operate effectively inside hierarchical, relationship‑based governance systems. It integrates four dimensions:
- Metacognitive: reflecting on and adjusting cultural assumptions.
- Cognitive: understanding social, legal and institutional norms.
- Motivational: valuing and engaging with cultural differences.
- Behavioural: adapting communication and actions to local expectations.
CQ acts as the bridge that allows leaders and practitioners to translate technical, medical and performance information into a form that aligns with the relationship and hierarchical values of Saudi and Jordanian (MENA) leadership.
3. The Practitioner’s Governance Toolkit
Success in hierarchical environments is rarely achieved through technical expertise alone. It depends on the ability to listen to subtle cues communicated by Team Managers and intermediaries. Often, the 20 percent of unspoken or indirect communication yields an 80 percent return in operational effectiveness and executive buy‑in.
Diplomatic skills, emotional literacy and cultural awareness are not soft skills; they are the skills that allow technical and medical professionals to navigate complex approval chains. These relationship competencies enable practitioners to translate performance and medical functions into precise, contextually appropriate language that influences decision‑making at the highest levels.
3.1 Medical Administrative Teams Access Points and Connectors

Table 2. Medical administrative teams act as access points and connectors, shaping approval pathways, timelines and continuity of care.
In Saudi and MENA systems, medical administrative teams shape access, prioritisation and continuity across the clinical pathway. They are often the first point of contact and the primary relationship access point between clubs, hospitals, consultants and insurers. Their influence determines the speed, clarity and stability of medical delivery, and they are the first contact point in the governance environment that practitioners must navigate.
4. Saudi Delivery Behaviour: Medical and Performance
4.1 Olympic and Federation Approval Chain
In Saudi Arabia, the Olympic Committee often initiates or validates performance and medical decisions. Federations act as the operational bridge, coordinating delivery and ensuring alignment with national priorities. Approvals move vertically, with reimbursement and authorisation can be fast tracked through federation advisors who act as trusted intermediaries. This creates a system where relational authority is as important as technical evidence.
4.2 Vertical Approvals for Medical and Injury Decisions
Medical decisions frequently require CEO or executive sign off, even when the issue is clinical. Non medical leaders can influence injury timelines, return to competition expectations and treatment pathways. Approvals move through relationships rather than departments, and the speed of decision making depends on trust, clarity and the perceived institutional impact of the decision.
5. Data Delivery Realities
Data systems remain variable in structure, access and maturity. Manual capture is common, and executive leaders often hold data ownership. Data literacy varies across clubs and federations, which affects how performance and medical information is interpreted. This creates a system where the narrative around data is as important as the data itself.
Centralised medical and performance systems, such as Athlete Management Systems (AMS) and Electronic Medical Records (EMR), aim to unify clinical, performance and operational information. EMR platforms focus on clinical documentation, while AMS platforms integrate wider performance, wellness and training data. Athletes typically interact through simple apps that allow them to log wellness, view schedules and access training programmes. These systems support decision making, but their effectiveness depends on adoption, data literacy and alignment with governance structures.
Data literacy across team members and athletes directly shapes daily operations, compliance and the effectiveness of medical and performance protocols. In Jordan, for example at Etihad Club, centralised athlete data, performance systems and medical platforms were not yet established, which meant that information moved through people rather than systems. Western European assumptions about capability can also slow or prevent the integration of centralised data systems. Capability is often equated with exposure, not competence, and if systems are not introduced clearly, contextually and with cultural intelligence, errors, repetition and low compliance follow. These are not region‑specific challenges; they are the foreseeable outcomes of introducing new systems into environments where governance, literacy and operational norms differ from Western models.

Figure 2. Cultural identity in sport is governed through formal approval pathways and leadership alignment
6. Cultural Delivery Constraints And Applied System Examples
Tribal approvals, HRH‑level influence, gendered access and institutional priorities shape how medical and performance decisions are made. These are structural and cultural realities that must be understood and respected. Effective delivery requires cultural intelligence and diplomatic communication.
Separate Example (Non‑Medical)
Ahead of the 2016 Olympic Games, approval for female athlete participation was sought through tribal and HRH leadership pathways, and the national dress worn at the opening and closing ceremonies was deliberately designed to represent all regions of the Kingdom. These processes were not symbolic; they reflected the formal pathways and national considerations required for representation on the world stage.
6.1 Medical Governance in Jordan Real System Examples
6.1.1 Case Study 1: Emergency Spinal Injury: Athlete 1

This case illustrates how emergency care interacts with institutional approvals within Jordanian club systems. The clinical pathway was clear, but the speed of delivery was shaped by governance rather than clinical urgency. The Director’s presence ensured continuity, upheld clinical standards and stabilised the pathway during a high-risk event.
Governance Barrier
Imaging and specialist access were dependent on HR, executive leadership and CEO approval. This is a feature of the system and applies even when red‑flag / acute injuries are present or when there is a history of previous hospitalisation. The approval chain is vertical, and it can introduce constraint at critical points.
Director Level Intervention
The Director’s involvement ensured spinal‑safe transfer, supported the hospital team during a period of limited capacity and maintained alignment between clinical need and institutional process. Without Director oversight, the pathway would have been slower, less coordinated and less controlled from a clinical governance perspective.
System Insight
This case demonstrates that medical decisions operate within institutional processes, not autonomously. Access points and connectors, particularly the sequence that moves from the Team Manager to HR and then to the CEO, determine the speed at which care can progress. Director involvement remains essential to protect safety, continuity and governance coherence.
Athlete Behaviour in Emergencies
Non‑injured athletes can unintentionally disrupt emergency protocol by moving injured athletes, crowding the injury site or removing athletes before assessment. This reflects an emerging ecosystem where professional standards are still developing. The Director’s role is to reinforce protocol, set expectations and protect the integrity of the medical process while supporting the medical team.
This case shows how emergency care interacts with institutional approvals in Jordan. The next case demonstrates how the same governance decisions shape specialist access, imaging and decision making in non‑emergency scenarios.

Incident and Response
During training, Athlete 2 sustained a nasal fracture following accidental contact. CT imaging at the hospital confirmed the injury, and medication was provided to reduce swelling ahead of specialist review. Three days later, the athlete disclosed a previous nasal fracture at the same site. The CT scan showed evidence of the old injury, but no treatment records were available to verify the history or previous management. The Performance Director supported the clinical reasoning, clarified the injury mechanism and aligned the next steps with the consultant’s recommendations.
Governance Barrier
The hospital’s administrative system, in conjunction with the Team Manager, scheduled the specialist appointment several days later, despite the consultant indicating that next‑day review was clinically appropriate. This delay reflected a structural gap between clinical need and administrative process, with administrative sequencing overriding clinical urgency.
Director Intervention
The Performance Director intervened to realign the pathway with clinical requirements. This included direct communication with hospital staff, clarification of the consultant’s recommendation and coordinated action to ensure the appointment was brought forward. Director presence ensured continuity, accuracy and protection of the athlete’s clinical timeline.
Team Manager Role
The Team Manager acted as the operational access point and connector, with other team managers also supporting throughout the process. Responsibilities included:
- booking appointments
- managing insurance
- attending the hospital
- communicating updates vertically to Executive Leadership and back down through the operational chain
- aligning operational decisions with the Director’s clinical direction
This role ensured that administrative processes, insurance approvals and hospital coordination moved at the required pace.
Governance Insight
This case demonstrates:
- operational dependence on the Team Manager as the primary connector
- the Director as the clinical authority within the governance structure
- hospital bureaucracy conflicting with clinical need
- the importance of Director presence at medical appointments
- real‑time decision support and relational diplomacy as essential components of safe care delivery
Why this matters: Administrative systems can distort clinical timelines unless Directors actively realign pathways. Case 3 shows how these same behaviours appear again, but with different consequences for safety, speed and decision making.
6.1.3 Case Study 3: Surgical Pathway: ACL Reconstruction Athlete 3

During the consultation, the Performance Director’s presence materially strengthened the clinical process. The consultant noted the Director’s professionalism, clinical knowledge and standards, commenting to his assistant that the Director’s note taking, questioning and medical language demonstrated competence and experience. As MRI scans were reviewed, the Director asked targeted clinical questions and provided context that shaped the consultant’s understanding of the athlete’s condition and injury mechanism. The physiotherapist was also present.
In Jordan, members of the medical team attending consultations is a new standard; historically, only team managers, who are non clinical, were present. This shift improved knowledge transfer, capability building and clinical alignment.
The consultant expressed confidence in the Director’s expertise and invited the Director to observe the surgical procedure. On the day of surgery, hospital administrative rules (Insurance) prevented entry into the surgical bay, but the Director met the surgeon pre operatively and provided critical information that influenced intra operative expectations. Significant pre‑operative work had been completed by the Director and physiotherapist, including monitoring the healing of knee structures, which had implications for what the surgeon would encounter and the extent of reconstruction required. The procedure proceeded as a full ACL reconstruction.
The Director remained present post operatively and at discharge, providing continuity for the club, Executive Leadership, team managers and the athlete’s family. This presence reinforced governance, ensured accuracy of communication and protected the athlete’s clinical pathway.
Parental Influence Meeting: ACL Injury (Separate to Consultation)
A separate meeting was held with senior club leadership, the Performance Director and the athlete’s parents after the family sought clarity on timelines and contacted leadership directly. Their concerns focused on the speed of the process and the expected date of surgery, which can be a pressure point in significant injuries where timing influences clinical outcomes.
The meeting centred on providing reassurance, clarity and structure. The Director outlined the full rehabilitation pathway, the surgeon’s clinical timelines and the return to competition protocol. It was explained that the timing of surgery is determined by the consultant surgeon based on clinical criteria, not by the club or the family. The Director also clarified that allowing the knee to heal before surgery leads to better operative conditions and improved post operative outcomes.
This protected the family’s wellbeing, stabilised expectations and safeguarded the organisation’s reputation. By balancing technical competence with cultural intelligence, the Director turned a potentially high risk clinical moment into an opportunity to build and strengthen trust across the system.
7. Building a Medical Network from Zero In Jordan
When I arrived in Jordan, the organisation’s medical landscape was still emerging, and formalised pathways, networks and integrated referral processes were not yet established. Clinical access relied on individual relationships, team managers and the national teams rather than a coordinated internal system. I began by understanding the environment, identifying what was already in place and clarifying where structured pathways would add value for the organisation.
7.1 Medical System Pathways Development
A network of five hospitals was established to provide consistent access to imaging, orthopaedics, emergency care and specialist consultations. A highly experienced team manager and the physiotherapist contributed recommendations, ensuring that local knowledge informed pathway development. This created a stable foundation for clear clinical decision making.
The club already worked with an external physiotherapy provider with a high quality facility and equipment, offering an environment with links to Al Hilal. This provider became an extension of internal capability and ensured that rehabilitation delivery met the expectations of a professional performance environment.
7.2 Relationship Building
A strong collaborative relationship developed between the organisation, the external physiotherapy provider and internal team members. Regular updates, videos and clinical progress were shared through coordinated communication, often facilitated by the team manager. This created an integrated approach to care and ensured that athletes received consistent, high quality support even when specialist equipment or full time physiotherapy coverage was not available internally.
The Performance Director attended most medical appointments, with attendance also rotating between medical and performance team members to support capability building and alignment.
7.3 Knowledge Transfer and Capability Building
For cases requiring expertise not available locally or nationally, I expanded into my existing international medical network. A complex shoulder case required specialist input, so I engaged Jo Gibson, a world‑class external expert, to guide the clinical pathway. I coordinated Jordanian physiotherapy care with the external provider to ensure alignment, continuity and a unified rehabilitation plan.
In line with Vision 2030’s focus on developing sustainable internal capability, I shared rehabilitation guides, Jo Gibson’s specialist rehabilitation principles and structured rehabilitation videos to support the development of internal practice. This ensured that local team members had access to high quality clinical reasoning frameworks and evidence based rehabilitation approaches, strengthening long term capability and reducing reliance on external expertise.
7.4 System Outcome
This network improved clinical governance, access and demonstrated that the organisation now had structured pathways supporting athletes, families and leadership. It also signalled that the club had a Director capable of building systems, establishing standards and creating the infrastructure required for long term stability.
8. UKSI vs Saudi–MENA: The Structural Misalignment
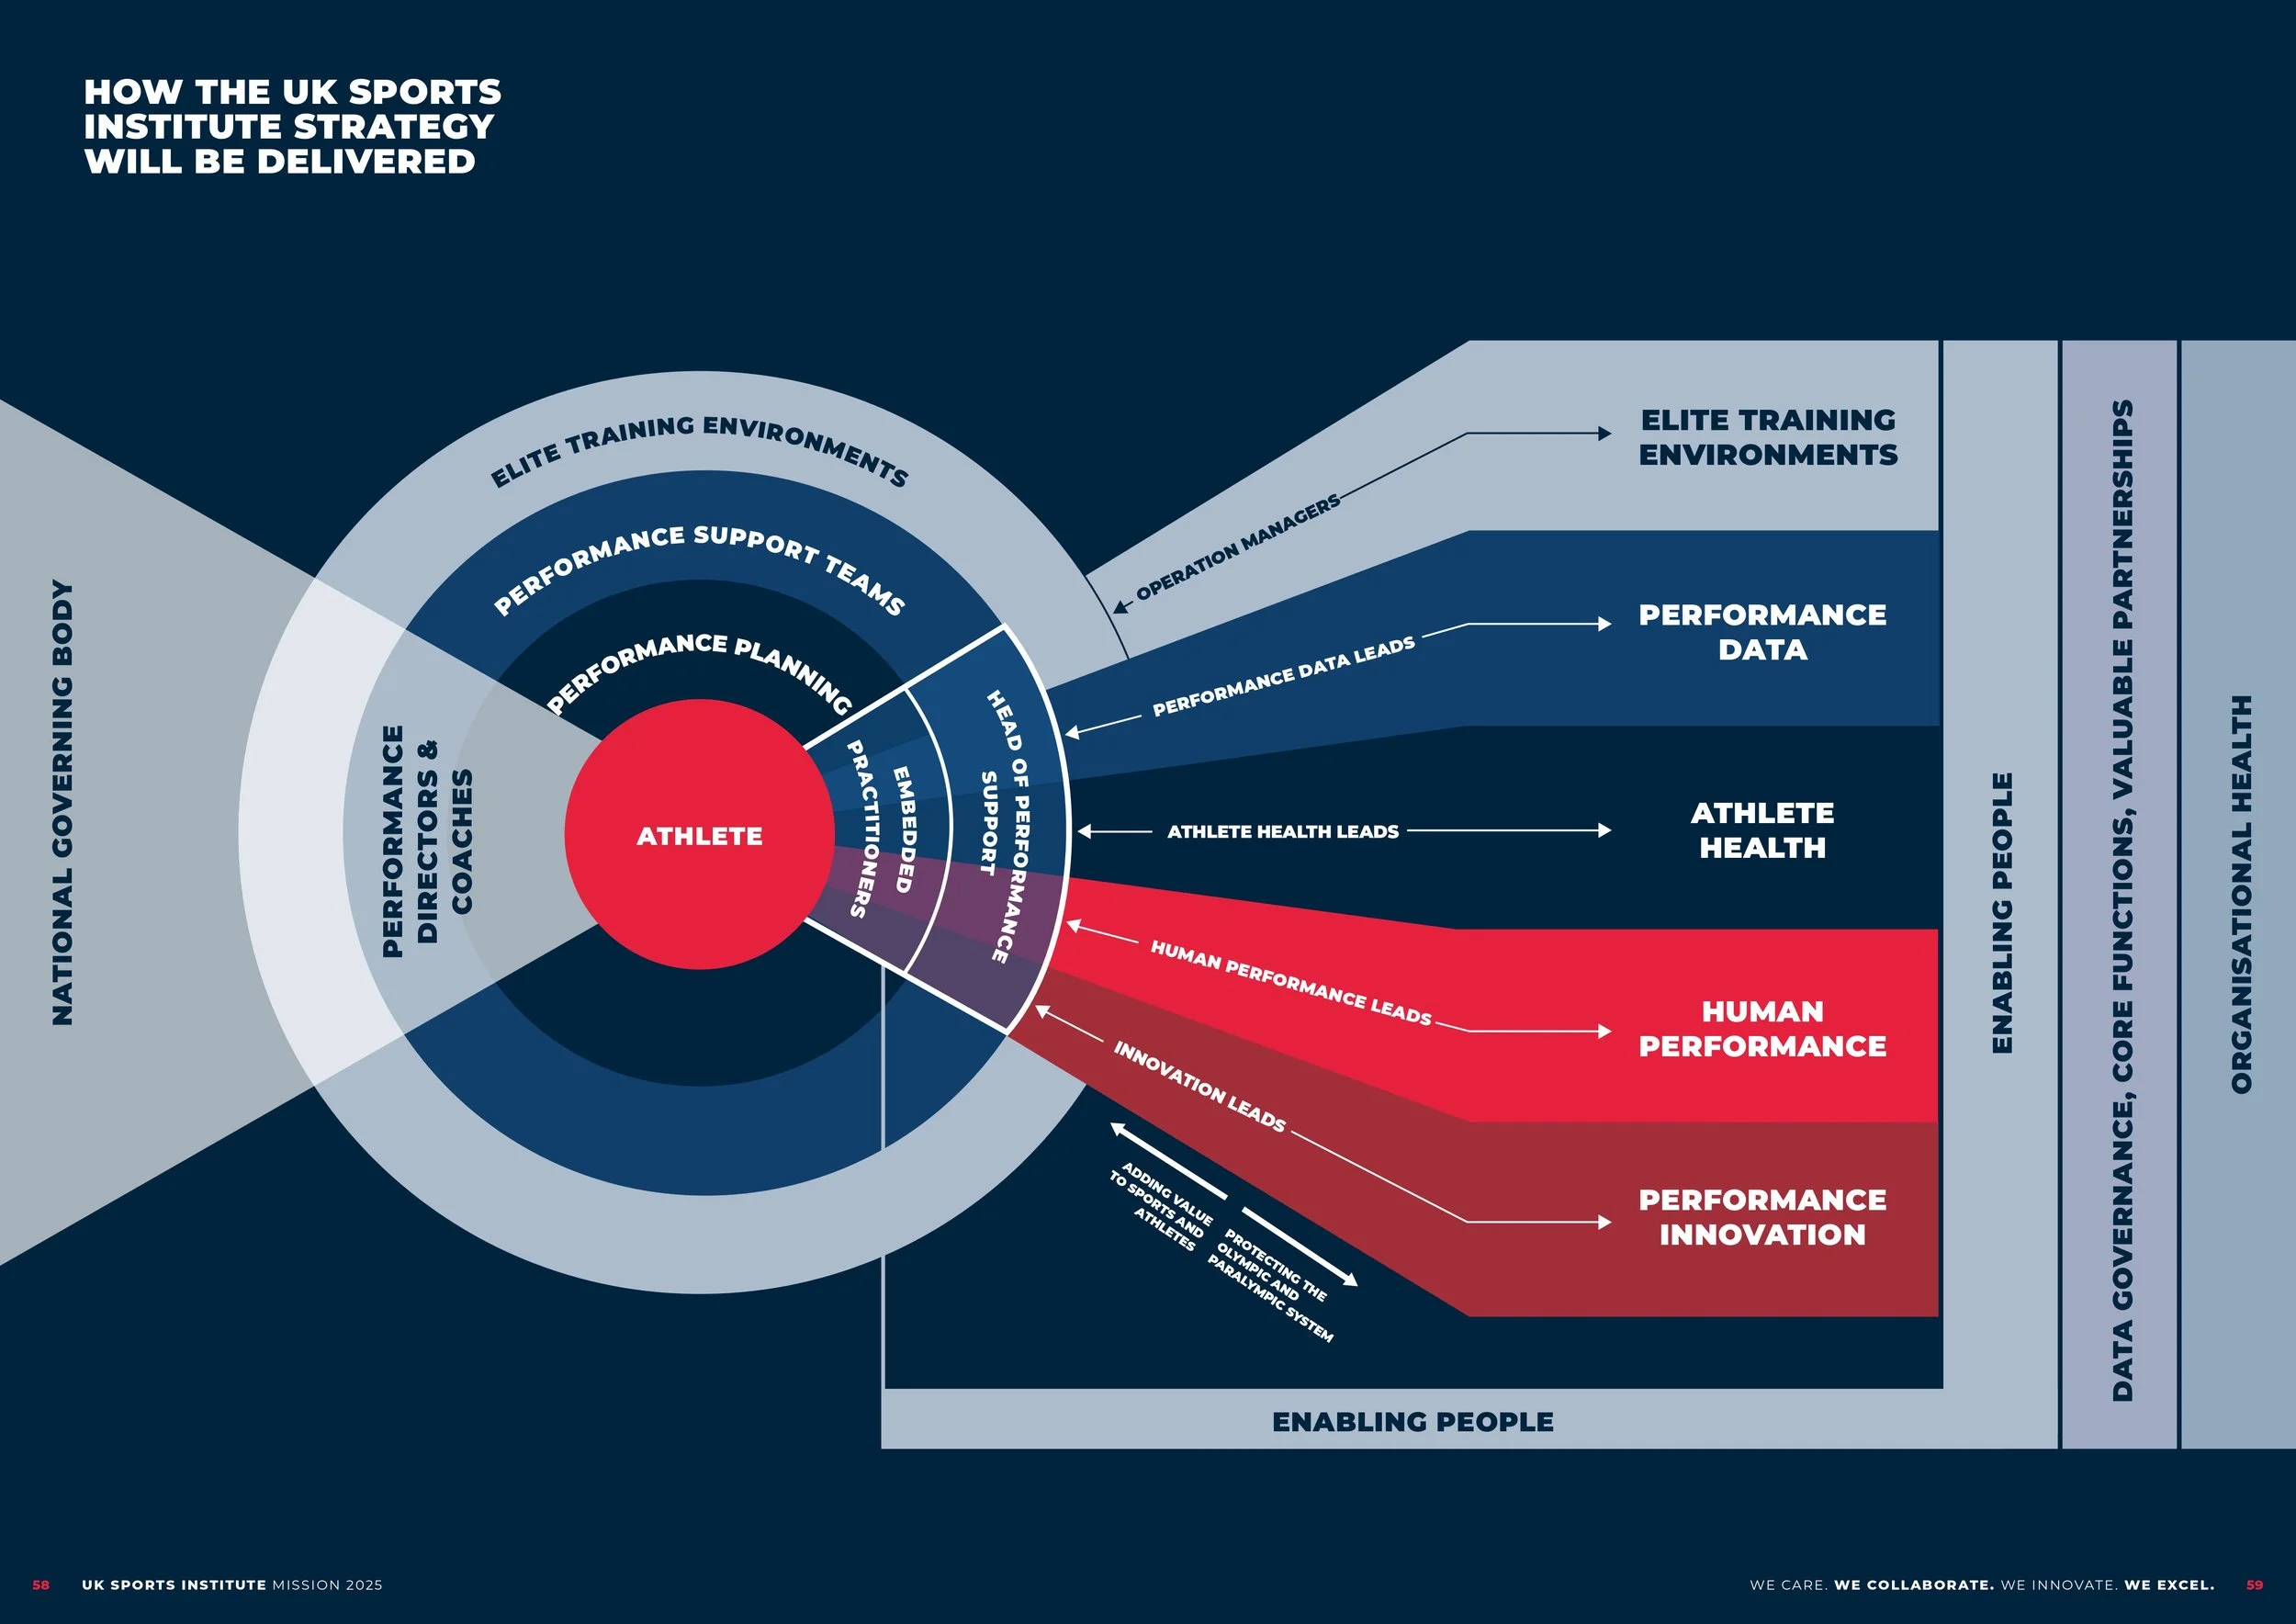
Figure 3. Structural contrast between athlete-centred UKSI pathways and vertically governed Saudi–MENA systems, highlighting differences in authority, data flow and decision-making
8.1 Structural Insight: When Leader Capability Becomes the System Ceiling
In many Saudi and MENA environments, leaders are assumed to be data literate, technologically capable and able to drive organisation wide adoption of AMS, EMR and performance systems. In practice, capability varies. When a leader is not fully confident in using these systems, the organisation may inherit that ceiling.
This creates structural constraint:
- systems are only partially implemented
- data is not democratised and sits across multiple platforms
- communication remains manual or fragmented, and compliance is low
- team members and athletes receive only the level of understanding the leader possesses
- organisational capability reflects individual capability, not system need
This is not a cultural issue. It is a governance, capability, and connection issue.
8.2 Interpretation for Leaders
This section demonstrates that UKSI models are structurally misaligned with the governance logic of Saudi and MENA systems.
Effective system design requires alignment with:
- vertical authority
- relational pathways
- executive influence
- institutional priorities
- cultural legitimacy
- capability based ceilings
The goal is not to impose systems into an environment, but to align system design so they function as natural, self sustaining extensions of the existing governance reality.
9. Transformation Requirements
Saudi and MENA systems do not require Western models to be imported; they require Western models to be built to align with the governance logic of the region. Transformation succeeds when system delivery aligns with this governance logic. This section outlines the structural requirements for building performance and medical systems that are stable and aligned with local and national priorities.
9.1 Executive Level Mandate and Ownership
System delivery in the region is driven by executive authority, not departmental autonomy.
Transformation requires:
- explicit executive mandate for Athlete Management Systems (AMS), Electronic Medical Records (EMR) and performance systems
- clear ownership at CEO or Executive Leadership level
- alignment with organisational priorities and national objectives
- visible endorsement that legitimises system use across teams
Without executive delivery accountability, systems remain symbolic, partial or siloed.
9.2 Relationship Pathways as Primary Delivery Channels
Delivery must move through the relationship pathways where authority operates.
Transformation requires:
- identifying the relationship access points that carry influence
- integrating these access points into communication and approval loops
- structuring delivery pathways that reflect relationship‑based authority
- ensuring information flows through the individuals who control decision‑making
Systems stall when they ignore the relationship pathways that govern decision flow.
9.3 Capability Ceilings and System Constraints
System delivery is constrained by the capability ceiling of those responsible for it.
This requires:
- assessing the capability ceiling of leaders responsible for system delivery
- providing targeted support, exposure and upskilling where needed
- ensuring systems do not exceed the capability of those expected to lead them
- delivering implementation plans that match actual, not assumed, capability
A system can operate above a leader’s capability level, but it will not operate effectively.
9.4 Institutional Authority as System Structure
Systems are defined by institutional authority and approval lines.
This requires:
- mapping institutional approval lines
- connecting and aligning system workflows with executive and federation processes
- ensuring data, reporting and decision‑making structures reflect institutional authority
- delivering systems that support national representation, not just performance outcomes
Systems succeed when they reinforce institutional legitimacy.
9.5 Succession Planning and Knowledge Retention
High turnover and evolving mandates destabilise both system continuity at the local level and institutional continuity at the organisational level.
Transformation requires:
- building structured succession pathways for key roles
- capturing institutional knowledge before individuals move
- ensuring continuity across Olympic cycles and competitions
- reducing dependency on single individuals or informal knowledge holders
Without succession planning, systems reset every time a leader moves.
9.6 Data Governance and System Integration
Data governance must be executive‑approved and operationally accessible.
This requires:
- executive‑approved data governance frameworks
- controlled but meaningful democratisation of data across teams and organisation
- integration of AMS and EMR systems across clubs, federations and national teams
- reducing fragmentation caused by multiple platforms and inconsistent compliance
Data must move from being an executive asset to an organisational capability.
9.7 Compliance Through Legitimacy
Compliance follows legitimacy, not policy.
Transformation requires:
- securing relational legitimacy before enforcing system use
- aligning compliance expectations with cultural norms
- using trusted intermediaries to drive adoption
10. Implementation Pathways
Implementation in Saudi and MENA environments succeeds when delivery reflects how authority, relationships and institutional priorities move in practice. Systems stabilise when implementation follows the pathways through which decisions and legitimacy flow. This section outlines how delivery behaves inside emerging performance and medical systems.
10.1 Executive‑Led Delivery Sequencing
Implementation begins at the point where authority is held. In Saudi and MENA systems, executive approval is not a final step, it is the starting point that determines pace, legitimacy and scope. Delivery moves only once leadership signals that the system is an organisational priority.
In practice, this involves:
- sequencing approval through executive lines before any operational implementation occurs
- establishing mandates early so teams understand the direction of travel
- aligning delivery timelines with federation, national team and seasonal cycles
Delivery stalls when departments attempt to implement before executive anchoring is secured.
10.2 Relationship Pathways as Delivery Channels
In relationship‑based governance systems, delivery moves through people before it moves through systems. Authority is exercised through trusted intermediaries, and implementation accelerates when these pathways are intentionally activated.
In delivery, this typically involves:
- identifying the relationship access points that carry influence
- embedding these individuals into communication and approval loops
- ensuring information flows through these intermediaries
- aligning implementation with relationship legitimacy
Delivery gains momentum when relationship pathways are treated as the primary mechanism of movement.
10.3 Capability‑Aligned Delivery
Implementation is constrained by the capability ceiling of those responsible for leading it. Systems stabilise when complexity is matched to leadership capacity and when capability gaps are addressed before system demands increase.
Operationally, this means:
- assessing capability levels before implementation
- sequencing delivery according to actual, not assumed, capability
- providing targeted exposure and support to leaders with delivery responsibility
- ensuring system complexity aligns with leadership capacity
A system can operate above a leader’s capability level, but it will not operate effectively.
10.4 Institutional – Organisation Integration Before Team Adoption
In Saudi and MENA systems, organisation authority precedes operational adoption. Teams cannot stabilise systems that are not yet endorsed, integrated or legitimised. Implementation succeeds when organisational workflows are aligned before team‑level use begins.
This typically involves:
- connecting system workflows with federation and executive processes
- ensuring reporting structures reflect institutional authority
- integrating AMS and EMR systems across clubs, federations and national teams
- establishing institutional legitimacy before operational adoption
Delivery fragments when teams adopt systems that institutions have not yet integrated.
10.5 Stabilisation Through Succession and Continuity
High turnover and evolving mandates destabilise both system continuity at the local level and institutional continuity at the organisational level. Implementation must therefore protect the relationships, knowledge and decision pathways on which systems depend.
In practice, this requires:
- embedding succession planning into system delivery
- capturing institutional knowledge at each transition point
- ensuring continuity across Olympic, seasonal cycles and competitions
- reducing dependency on single individuals or informal authority structures
Delivery stabilises when capability and knowledge remain within the institution, not within individuals.
10.6 Data Governance as a Delivery Enabler
Data becomes a delivery enabler only when governance, access and interpretation align with authority. In emerging systems, data must be both executive‑approved and operationally usable to support decision‑making.
Operationally, this involves:
- executive‑approved data governance frameworks
- controlled but meaningful data access across teams
- integration of data systems to reduce fragmentation
- establishing clear data ownership, flow and accountability
Delivery becomes efficient when data supports decision‑making across the organisation.
10.7 Compliance Through Legitimacy
Compliance follows legitimacy, not enforcement. In relationship‑based systems, adoption is secured through trust, cultural alignment and trusted endorsement rather than policy pressure.
10.8 Frameworks for Delivery in Emerging Systems: Medical and Performance
Emerging systems stabilise through applied frameworks that reflect how authority, information and decisions move in practice. This section translates lived experience across Saudi Arabia and Jordan into practical, governance‑aligned models that leaders can use immediately. Each framework is grounded in the actual approval chains, communication loops and medical and performance behaviours that operate inside evolving systems. These are not Western models adapted for the region; they are Saudi‑first and regionally grounded.
11. Vertical Approval Map in Saudi Arabia and Jordan
In both Saudi Arabia and Jordan, decisions move vertically rather than laterally. Authority sits with leadership, not departments. This is the defining structural difference between mature Western systems and emerging systems across the MENA region.
In Saudi Arabia, approvals move through formal governance layers: federation leadership, SOPC departments and senior oversight.
In Jordan, approvals move through relationship hierarchies: physiotherapist, team manager, coach, club leadership and investors.
Understanding this structure is fundamental. It determines speed, legitimacy and system stability.
11.1 Federation and Olympic Delivery Loop in Saudi Arabia
Saudi Olympic delivery follows a centralised approval loop:
- the Olympic Committee identifies the need and confirms funding
- the federation validates requirements and approves budgets
- the federation pays first and the SOPC reimburses (see earlier points)
- delivery is coordinated across coaches, athletes, federation advisors and SOPC departments
This loop explains why alignment, not autonomy, drives system stability in Saudi sport, and why decentralised Western models do not transfer directly.
11.2 Club Performance Governance Model in Jordan
Jordanian clubs operate through relationship‑based governance rather than structural governance. Etihad provides a clear illustration:
- Board members and investors can hold veto power
- Technical Directors may also serve as Head Coaches, concentrating authority in individuals
- The Performance Director influences decisions within the governance structure
- The Team Manager acts as the operational and cultural bridge between departments
This model shows why stabilisation depends on relationship building, clarity of communication and structured reporting rather than structural reform.
11.3 Athlete Availability Decision Pathway
In emerging systems, athlete availability is institution‑centred rather than athlete‑centred.
In Saudi Arabia, national team priorities can override club needs, and availability decisions follow formal governance channels.
In Jordan, readiness decisions are shaped by relationship legitimacy, trust and influence. Coaches may request athletes to train despite injury risk. Team managers mediate. Physiotherapists navigate expectations. The Performance Director advocates for safety and readiness, but final decisions are shaped by relationship dynamics and governance realities.
Cases involving groin injuries, Achilles tendinopathy and stress fractures demonstrate why Western models do not transfer directly. The decision‑maker differs, and the approval pathway is vertical rather than clinical.
Western high‑performance systems are designed to be athlete‑centred, but even they shift toward institutional priorities under pressure. The difference is that in Saudi and Jordan, the organising principle is structurally institution‑centred from the outset.
11.4 Data Maturity Ladder in Saudi Arabia and Jordan
Emerging systems progress through four stages:
- manual communication through WhatsApp and verbal updates
- disconnected systems, including standalone platforms and shared documentation tools (e.g. Google Docs)
- semi‑integrated workflows across teams
- fully aligned, governance‑approved data flow
A system becomes high‑performance only when its data is governance‑coherent and meaningfully accessible across the organisation. Technology does not determine system maturity; governance alignment does.
11.5 Cultural Intelligence Operating Principles
Operating effectively inside Saudi and Jordanian systems requires cultural intelligence: respect for authority, relationship legitimacy, rationale‑based communication, translation of intent, anticipation of delays and avoidance of Western assumptions about autonomy, data and decision‑making. Cultural intelligence is the operating system of emerging performance environments.
11.6 Stabilised Progression Model
Emerging systems stabilise in four phases:
- foundations built on relationships, legitimacy and basic reporting
- integration of workflows, pathways and communication loops
- complexity added through data governance and multi‑team alignment
- optimisation through performance modelling, predictive systems and institutional maturity
Systems must stabilise before they can scale. This is the core principle of Saudi‑first and MENA system design.
11.7 The Strategic Shift in the Next Phase
Saudi sport is entering a new phase. The first decade of Vision 2030 relied on state‑driven investment to build capability, create infrastructure and generate national momentum. The shift from state wealth to system wealth is now required, with federations, clubs and performance environments building stability, capability and competitive advantage through their own pathways rather than continuous external support.
This shift is already visible: funding is tightening. Expectations on governance are rising. Accountability for performance is increasing. Federations are now expected to demonstrate sustainability, medal efficiency and the ability to convert investment into capability.
The next phase of Vision 2030 will reward systems that operate with clarity, alignment and financial discipline. The goal is to position performance as an institutional asset, ensuring the legacy of Vision 2030 is defined not only by infrastructure, but by the sustainable systems that operate within it.
11.8 What Comes Next: From State Wealth to System Wealth
Next week’s edition introduces a comparative European performance pathway model that has not been surfaced in the region. It examines how several smaller European nations delivered high medal efficiency at the Paris Olympics without reliance on centralised national institutes, with federations retaining ownership of performance pathways and national bodies acting as coordinators rather than central authorities. This model offers a relevant reference point for Saudi federations preparing for the next phase of system development.
The full pathway structure and governance model will be outlined in detail in the next edition. This document reflects applied experience across Saudi Arabia and Jordan and is intended to support governance‑aligned system design in emerging performance environments.